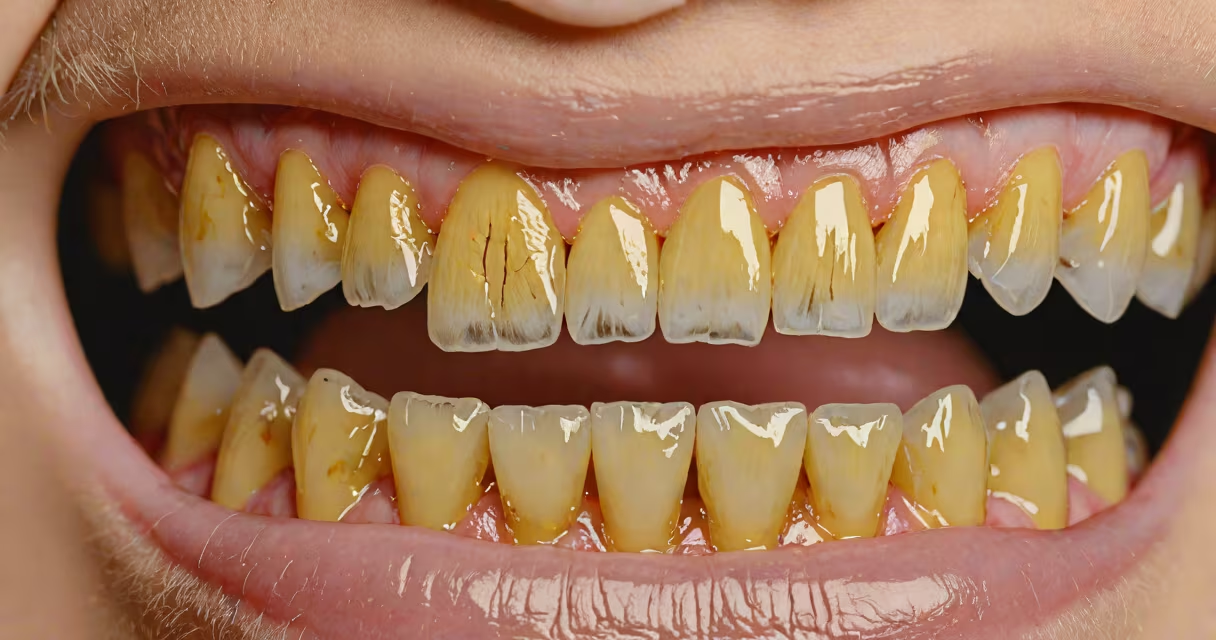
Tartar buildup on teeth, also known as dental calculus, is calcified plaque that forms on tooth surfaces when bacterial biofilm mineralizes due to exposure to saliva and gingival crevicular fluid. Once formed, it cannot be removed by brushing or flossing and requires professional dental intervention.
Tartar begins as soft plaque-a sticky film of bacteria, food debris, and salivary proteins that accumulates on teeth within hours after eating. Over time, minerals in saliva such as calcium and phosphate precipitate into the plaque matrix, hardening it into calculus. This process typically takes 24 to 72 hours to begin, but visible tartar usually appears after several days to weeks of poor oral hygiene.
According to the American Dental Association (ADA), tartar forms most frequently along the gumline, especially on the inner surfaces of lower front teeth and the outer surfaces of upper molars. Its presence is a major contributor to periodontal disease progression. The National Institute of Dental and Craniofacial Research (NIDCR) notes that untreated tartar increases the risk of gingivitis, periodontitis, and eventual tooth loss.
Plaque forms continuously on teeth, particularly in areas difficult to reach with a toothbrush-like between teeth, near the gumline, and around dental restorations. Bacteria in plaque metabolize sugars and produce acids that erode enamel and irritate gums. As plaque sits, it absorbs calcium and phosphorus from saliva, undergoing a process called mineralization.
Mineralization transforms soft, translucent plaque into hard, porous, and often discolored calculus. The color ranges from white to yellow, then dark brown or black as it ages and incorporates pigments from food, tobacco, or blood. Tartar deposits grow layer by layer, creating rough surfaces that attract more plaque and bacteria, forming a feedback loop of deterioration.
A 2021 study published in the Journal of Clinical Periodontology found that individuals who brush less than twice daily and skip flossing have 3.6 times higher odds of developing subgingival calculus compared to those with consistent oral care routines. This confirms that mechanical removal of plaque is essential to prevent tartar formation.
Tartar occurs in two primary forms based on location:
| Type | Location | Appearance | Risk Level |
|---|---|---|---|
| Supragingival | Visible above the gumline | Yellow or white, often on molars and front teeth | High-leads to gingivitis and bad breath |
| Subgingival | Beneath the gumline, below the visible gum tissue | Dark brown or black, often undetectable without probing | Very high-drives periodontitis and bone loss |
Subgingival tartar is more dangerous because it lies hidden beneath the gum tissue. It creates pockets between teeth and gums where bacteria thrive, causing inflammation, bleeding, and irreversible damage to the supporting structures of teeth. These pockets trap more debris and resist home care, making professional cleaning critical.
One non-obvious fact: tartar does not form uniformly. It tends to accumulate faster in areas with reduced salivary flow, such as behind wisdom teeth or near dry mouth conditions caused by medications. People taking antihypertensives, antidepressants, or antihistamines are at increased risk due to xerostomia (dry mouth).
Many patients confuse tartar with stains or decay. Stains result from external substances like coffee, tea, or tobacco and can be removed with whitening treatments. Decay involves demineralization of enamel and dentin, leading to cavities. Tartar, however, is a structural deposit that alters the tooth's surface and supports infection.
Another common error is assuming that brushing harder removes tartar. Aggressive brushing damages enamel and gums without affecting calcified deposits. The ADA warns against using abrasive toothpastes or excessive pressure, which can lead to abrasion and recession, worsening gum exposure and tartar access.
I once observed a patient who believed she was preventing tartar by brushing twice daily with a hard-bristled toothbrush. After six months, her dentist discovered extensive subgingival calculus and early periodontal pockets. Switching to a soft brush and adding interdental cleaning reversed the trend. This illustrates that frequency alone doesn't prevent tartar-it's proper technique and tools that matter.
Preventing tartar buildup relies on consistent plaque control. Brushing twice daily with fluoride toothpaste and flossing daily disrupts plaque before mineralization. Using an electric toothbrush with a pressure sensor reduces the risk of damaging gums while improving plaque removal efficiency.
Interdental cleaning tools-such as water flossers, oral irrigators, or interdental brushes-are effective at removing plaque from tight spaces where bristles can't reach. A 2019 Cochrane review concluded that water flossers reduce gingivitis by 15% more than string floss over six months, especially in people with orthodontic appliances.
Once tartar forms, only a dental professional can remove it. Scaling uses ultrasonic or hand instruments to break apart and scrape off calculus. Root planing smooths the root surface to eliminate bacterial reservoirs and promote gum reattachment. These procedures are typically performed during routine cleanings or periodontal therapy.
For severe cases, laser-assisted periodontal therapy may be used. A 2022 study in the International Journal of Dental Hygiene showed that Nd:YAG lasers reduced subgingival calculus by 40% more than traditional scaling alone, though results depend on operator skill and equipment calibration.
If you're experiencing sensitivity or discomfort from tartar, using Anbesol for teeth may provide temporary relief from pain associated with inflamed gums-but it does not treat the underlying cause. Addressing tartar requires professional care, not topical remedies.
Signs of tartar include visible yellow or brown deposits, persistent bad breath, red or swollen gums, and bleeding during brushing. If you notice any of these, schedule a dental exam. Most dentists recommend professional cleanings every six months, but individuals with high risk factors-such as diabetes, smoking history, or genetic predisposition-may need visits every three to four months.
Early detection prevents irreversible damage. Untreated tartar leads to pocket depths exceeding 4mm, which increases the likelihood of requiring surgical intervention. The NIDCR estimates that 47% of adults aged 30 and older in the U.S. have moderate to severe periodontitis, often linked to untreated tartar.
Understanding tartar buildup is important for long-term oral health. It's not just a cosmetic issue-it's a medical condition that can compromise both teeth and systemic health. Regular dental visits and consistent home care are the only ways to stop its progression.
Prevention starts with daily habits. Removing plaque before it calcifies stops tartar before it forms. If you already have deposits, professional cleaning is the only effective solution. Ignoring tartar risks not just your smile, but your well-being.