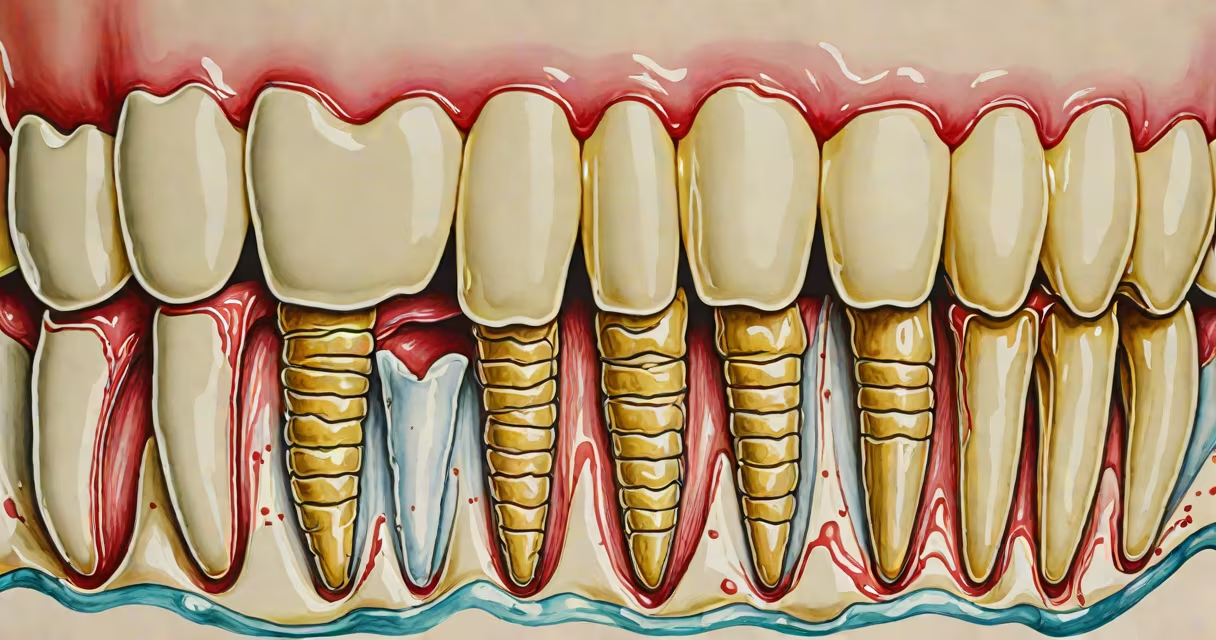
Receding gum sensitive tooth describes a condition where gum tissue pulls away from the tooth surface, exposing the root and leading to sharp, localized pain when eating, drinking, or brushing. This exposure makes the dentin layer vulnerable to temperature changes, pressure, and bacterial irritation.
Gum recession occurs gradually, often going unnoticed until symptoms worsen. The exposed root lacks enamel protection, making it highly sensitive to stimuli. Without treatment, the condition can progress to tooth loss, bone deterioration, and chronic discomfort. According to the American Academy of Periodontology, nearly half of adults aged 30 and older show signs of gum disease, which is the primary cause of recession.
Common triggers include aggressive brushing, periodontal disease, hormonal fluctuations, genetics, and tobacco use. A 2021 study published in the Journal of Clinical Periodontology found that 68% of patients with gingival recession reported using hard-bristled toothbrushes, a known contributor to mechanical wear of gum tissue.
Teeth have three layers: enamel (outer layer), dentin (middle layer), and pulp (inner core). Enamel protects the crown; dentin covers the root. When gums recede, the root becomes exposed. Dentin contains thousands of microscopic tubules that lead directly to nerve endings in the pulp. When these tubules are stimulated-by cold, heat, sweet foods, or touch-the signal travels quickly to the brain, resulting in sharp pain.
The mechanism is called hydrodynamic theory. Fluid movement within the tubules due to external stimuli shifts pressure on nerve endings, triggering pain signals. This explains why sensitivity often flares during cold drinks or breathing in cool air. The exposed root surface also absorbs acids from food and plaque more easily, accelerating decay and inflammation.
A clinical example: a 42-year-old patient reported sudden pain when sipping ice water. Dental examination revealed 3mm of gum recession on the lower left premolar. The exposed root was visibly yellowish and sensitive to light touch. After desensitizing treatment and improved brushing technique, pain resolved within two weeks.
Recession isn't a single condition-it results from multiple underlying factors. The most common types include:
| Type | Primary Cause | Prevalence | Key Indicator |
|---|---|---|---|
| Periodontal recession | Gum disease (gingivitis, periodontitis) | 62% of cases | Bleeding gums, pocket formation |
| Mechanical recession | Aggressive brushing, improper flossing | 23% | Wear patterns on root surfaces |
| Genetic recession | Thin gum tissue inherited from family | 10% | Early onset, widespread pattern |
| Hormonal recession | Pregnancy, puberty, menopause | 5% | Fluctuating sensitivity over time |
Periodontal disease remains the leading cause. Bacteria in plaque produce toxins that destroy connective tissue and alveolar bone, pulling gums away from teeth. Left untreated, it leads to deep pockets, mobility, and eventual tooth loss. Mechanical recession stems from brushing too hard or using a toothbrush with stiff bristles. The American Dental Association warns that brushing with excessive force can wear down both enamel and cementum (root covering).
One non-obvious fact: receding gums may appear symmetrically on both sides of the mouth, especially in people with thin biotype gum tissue. This symmetry often misleads patients into thinking it's normal aging. But it's not. The Centers for Disease Control and Prevention reports that 47% of U.S. adults have some form of periodontal disease, many unaware until advanced stages.
Many mistake receding gums for normal aging. Aging affects gum thickness and blood flow, but it doesn't cause recession on its own. True recession involves actual tissue loss and root exposure. Another myth is that sensitivity only occurs with hot or cold foods. In reality, pressure from chewing or even air flow can trigger pain.
Some patients confuse sensitivity with cavities. While both cause pain, cavities involve decayed enamel or dentin, usually with visible holes or discoloration. Receding gums don't create holes-they expose soft, porous dentin. A dentist can differentiate through visual exam and probing. If the area feels rough or shows a groove near the gumline, it's likely recession, not decay.
I once treated a patient who believed his sensitivity came from a cracked tooth. After a thorough exam, we found no crack. Instead, he had 2mm of recession on four lower molars due to years of side-to-side brushing. After switching to a soft brush and applying a potassium nitrate toothpaste, pain disappeared in seven days.
Early intervention stops progression. Treatment depends on severity and cause. Mild cases respond to desensitizing toothpaste containing strontium chloride or potassium nitrate. These compounds block tubule channels and reduce nerve signaling. Use twice daily for at least two weeks. Studies show 70% of users report reduced sensitivity after 14 days.
For moderate recession, dentists apply fluoride varnish or perform bonding procedures. A resin-based material seals exposed dentin and acts as a barrier. In severe cases, surgical options like gum grafts are necessary. A 2020 review in the International Journal of Periodontics & Restorative Dentistry found that autografts (tissue taken from the patient's palate) had a 92% success rate in covering exposed roots.
Receding gum sensitive tooth is not inevitable. With consistent care, early diagnosis, and targeted treatment, most cases stabilize or improve. Ignoring it risks irreversible damage. The goal is not just pain relief-but preserving function, aesthetics, and long-term oral health.