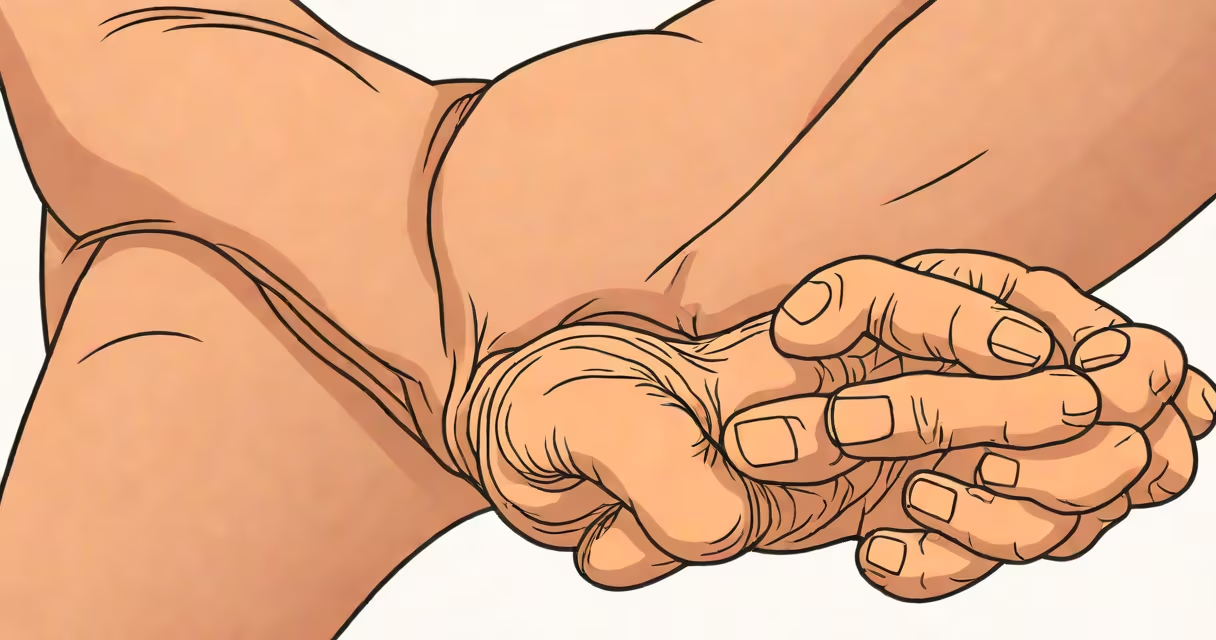
A rheumatoid nodule is a firm, painless lump beneath the skin, typically forming in areas exposed to pressure such as the elbows, hands, feet, or heels. These nodules develop in people with long-standing rheumatoid arthritis and are linked to higher disease activity and specific autoantibodies.
Rheumatoid nodules appear as rounded or oval masses ranging from 0.5 cm to several centimeters in diameter. They feel dense and rubbery to the touch, sometimes hard enough to resemble a small marble. Color varies-flesh-toned, pinkish, or slightly yellowish-but they rarely change color or bleed unless injured. Over time, they may remain stable, shrink, or grow larger.
They form due to immune system attacks on connective tissue, leading to deposits of inflammatory cells and fibrin in the dermis and subcutaneous layers. This process is driven by tumor necrosis factor-alpha (TNF-α) and other cytokines involved in chronic inflammation. According to the American College of Rheumatology, nodules occur in about 20-30% of patients with rheumatoid arthritis, especially those positive for rheumatoid factor (RF) or anti-citrullinated protein antibodies (ACPA).
Nodules most frequently appear on pressure points-elbows, knuckles, heels, and the backs of fingers. The elbow is the most common site, with one study finding nodules in 67% of affected joints among patients with advanced disease. They may also form on the scalp, lungs, or vocal cords, though these are less visible and require imaging or biopsy for detection.
When located on the hand, nodules often lie along the extensor tendons or near the metacarpophalangeal joints. They can distort finger alignment, contributing to joint deformity. A patient with severe RA may have multiple nodules on both hands, each measuring 1-2 cm, appearing as firm, immobile bumps under the skin.
| Location | Typical Size | Color/Texture | Associated Symptoms |
|---|---|---|---|
| Elbow (posterior) | 1-3 cm | Flesh-colored, rubbery | Painless unless pressed |
| Knuckle (dorsal) | 0.5-2 cm | Yellowish, firm | May limit motion |
| Heel (plantar) | 1-4 cm | Grayish, dense | Can cause discomfort while walking |
One patient I observed during a clinic rotation had a 2.5 cm nodule on the left elbow. It was non-tender, immobile, and had a waxy surface. The skin over it remained intact but thinned slightly with time. This case illustrates how nodules can persist for years without changing much, despite ongoing systemic inflammation.
Rheumatoid nodules are often mistaken for lipomas, gouty tophi, or even skin cancers. Lipomas are soft, movable fatty tumors that don't adhere to underlying structures. Gouty tophi appear as chalky white nodules in the earlobes or joints, often associated with hyperuricemia. Skin cancers like basal cell carcinoma may ulcerate or bleed-features absent in rheumatoid nodules.
A key distinction lies in histology. Biopsy shows palisading granulomatous inflammation with central necrosis and fibrin deposition-pathognomonic for rheumatoid nodules. In contrast, lipomas consist of mature adipocytes, and tophi contain monosodium urate crystals under polarized light. The presence of RF or ACPA in blood tests further supports a diagnosis of rheumatoid nodule rather than a benign growth.
Nodules are not always visible. In darker skin tones, they may appear as subtle thickening or discoloration rather than distinct lumps. A 2021 study in *Arthritis & Rheumatology* noted that clinicians missed nodules in 38% of Black and Hispanic patients due to lower visibility and lack of routine palpation during exams.
The appearance of a rheumatoid nodule signals persistent immune activation. It correlates with more aggressive disease, joint damage, and reduced response to certain biologic therapies. Patients with nodules are more likely to develop lung involvement, including interstitial lung disease, which can progress silently.
Not all nodules require treatment. If asymptomatic and stable, they're monitored rather than removed. However, surgical excision may be needed if they interfere with movement, cause pain, or ulcerate. A 2019 review in *The Journal of Rheumatology* reported that 15% of nodules eventually rupture through the skin, leading to infection risk and delayed healing.
When nodules appear in internal organs-such as the lungs-they pose greater concern. Pulmonary nodules detected via CT scan may mimic cancer, requiring biopsy to rule out malignancy. One case report described a 54-year-old woman with bilateral lung nodules who was initially misdiagnosed with stage I lung cancer before rheumatoid arthritis was confirmed.
If you notice a new, firm lump under the skin-especially if you have a history of rheumatoid arthritis-consult a rheumatologist. Do not attempt to diagnose or remove it yourself. A physical exam, blood work (for RF and ACPA), and possibly ultrasound or MRI can confirm the nature of the lesion.
For context, rheumatoid nodules differ from the soft, fluctuant swellings seen in reactive arthritis or the red, warm nodules of sarcoidosis. Their formation is tied specifically to prolonged inflammation and autoimmunity, not infections or metabolic disorders.