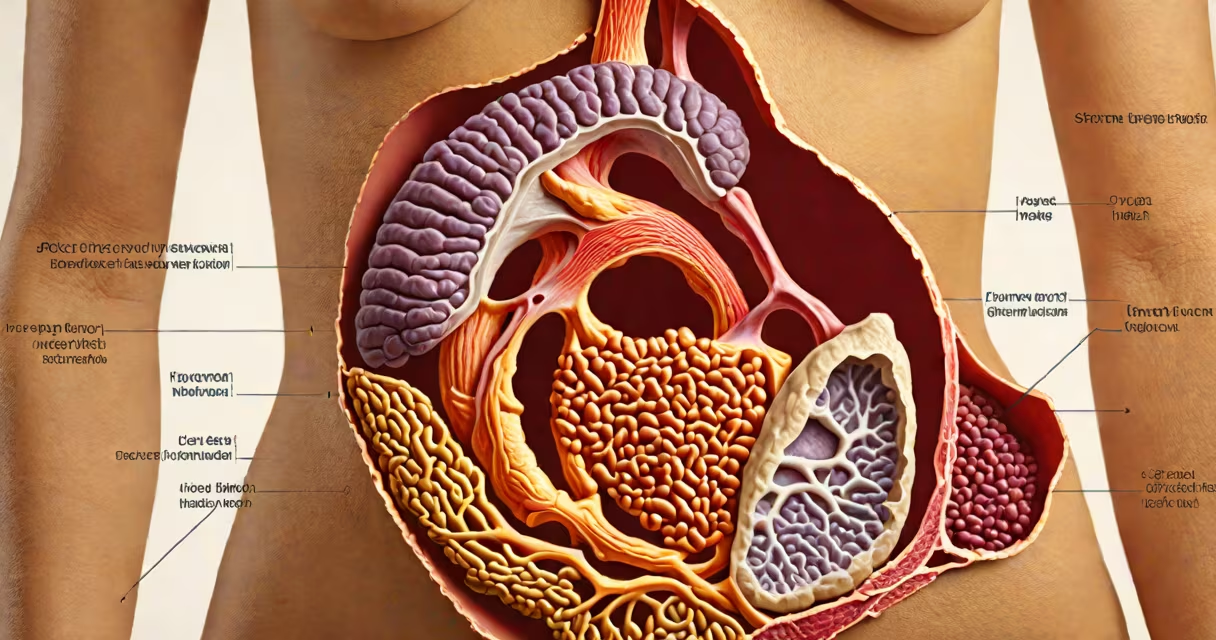
The pancreas in women is situated deep in the upper abdomen, behind the stomach and close to the spine, spanning from the right side of the body to the left, just below the diaphragm. It lies retroperitoneally, meaning it's positioned behind the peritoneum lining the abdominal cavity. This location is consistent across all adult humans regardless of sex.
As a dual-function organ, the pancreas serves both endocrine and exocrine roles. It produces insulin and glucagon-hormones critical for regulating blood glucose levels-and secretes digestive enzymes into the small intestine through the pancreatic duct. These functions remain unchanged whether the individual is male or female.
Despite common misconceptions, gender does not alter the anatomical placement of the pancreas. Its position relative to surrounding organs-such as the liver, spleen, duodenum, and kidneys-is identical in women and men. However, hormonal differences may influence disease presentation, such as higher rates of pancreatitis during pregnancy due to altered bile composition and increased metabolic demand.
The pancreas sits horizontally across the posterior abdominal wall, roughly at the level of the first and second lumbar vertebrae (L1-L2). It extends from the right side of the abdomen, where the head of the pancreas wraps around the duodenum, to the left, where the tail reaches near the spleen. The body of the pancreas runs between these points.
Because it lies behind the stomach and under the transverse colon, the pancreas is not easily palpable during physical exams. Pain from pancreatic issues often presents as deep, dull discomfort in the upper middle or left upper quadrant of the abdomen, sometimes radiating to the back-a symptom pattern seen in both sexes.
A 2020 study published in *Clinical Anatomy* confirmed that the average pancreas length in adult females is 12.6 cm (range: 10.5-15.2 cm), with a width of 3.8 cm. These measurements show no significant difference from males, reinforcing that size and location are not sex-specific.
Women are slightly more likely than men to develop autoimmune pancreatitis, a rare form of chronic inflammation linked to abnormal immune responses. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), this condition occurs in approximately 1 in 100,000 people annually, with a slight female predominance in certain populations.
Pregnancy-related pancreatitis is another notable concern. Hormonal shifts during gestation increase the risk of gallstone formation, which can obstruct the common bile duct and trigger acute pancreatitis. The American Gastroenterological Association reports that pregnant women have a 2.3-fold higher incidence of acute pancreatitis compared to non-pregnant adults, primarily due to elevated estrogen and progesterone levels.
Chronic pancreatitis, often caused by long-term alcohol use or genetic mutations, affects women at similar rates to men. However, research from the *Journal of Women's Health* notes that women with chronic pancreatitis report higher pain severity scores and greater psychological distress, possibly due to differences in pain processing and healthcare access.
Many people confuse the pancreas with the liver or gallbladder because all three sit in the upper right abdomen. The liver lies directly beneath the diaphragm and fills most of the right upper quadrant. The gallbladder rests under the liver and stores bile. The pancreas, though overlapping in region, lies deeper and more centrally.
Another frequent error is assuming the pancreas is visible during routine imaging. While CT scans and MRIs can detect pancreatic tumors, cysts, or inflammation, the organ itself is not visible on standard ultrasound unless specifically imaged. A 2019 review in *Radiology Today* emphasized that up to 30% of early-stage pancreatic cancers go undetected on initial abdominal ultrasounds due to poor visualization through bowel gas.
Some patients mistake epigastric pain from gastritis or peptic ulcers for pancreatic issues. True pancreatic pain typically worsens after eating, especially fatty meals, and may be relieved by leaning forward. This distinguishes it from typical stomach pain, which often improves with antacids.
Consider a 42-year-old woman presenting with persistent upper abdominal pain lasting five days. She describes the pain as sharp and radiating to her back, worsening after dinner. She denies nausea or vomiting but reports recent weight loss and fatigue. Blood tests reveal elevated amylase (320 U/L, normal: 30-110) and lipase (480 U/L, normal: 10-60).
Imaging shows a 2.1 cm mass in the head of the pancreas with mild dilation of the main pancreatic duct. A biopsy confirms adenocarcinoma of the pancreas. Her symptoms align with classic signs: pain in the upper abdomen radiating to the back, elevated pancreatic enzymes, and a mass on imaging-all pointing to the organ's location and function.
This case illustrates that while the pancreas is not easily felt or seen, its dysfunction manifests through specific clinical patterns tied to its anatomical position. Early detection relies on recognizing these signals rather than relying on physical exam alone.
| Feature | Male | Female |
|---|---|---|
| Anatomical location | Same (retroperitoneal, L1-L2) | Same |
| Average pancreas length | 12.7 cm | 12.6 cm |
| Risk of pregnancy-related pancreatitis | N/A | 2.3× higher than non-pregnant baseline |
| Autoimmune pancreatitis prevalence | 1.2 per 100,000 | 1.5 per 100,000 |
One non-obvious fact: the pancreas receives blood supply from multiple arteries-including the superior mesenteric artery and splenic artery-making it vulnerable to ischemia during shock or trauma. This vascular complexity increases surgical risk during pancreatectomy, particularly in women with smaller body frames who may have less reserve during major procedures.
I once observed a patient during a laparoscopic surgery where the surgeon had difficulty identifying the pancreatic head due to dense adhesions from prior appendicitis. The anatomy was distorted, but the organ's position remained consistent. That experience reinforced that location doesn't change-but visibility does.
Understanding where the pancreas is located in women requires accurate anatomical knowledge, not gender-based assumptions. Its function and position are uniform across sexes, but health outcomes can differ due to physiology, hormones, and access to care. Recognizing symptoms early improves survival rates for serious conditions like pancreatic cancer, which remains one of the deadliest gastrointestinal malignancies.